

Signs of pneumonia: Sometimes vague and unexpected

Using a vibration plate: What it can — and can't — do for your body
The surprising link between ovarian cancer and the fallopian tubes

People who walk more or walk faster live longer, study finds

For sleep apnea, a dental device may be as effective as CPAP

Rosacea treatments: What works?

Carb cycling: What is it, and does it work?

Salmonella, E. coli, Cyclospora, and other germs that cause food poisoning: What you need to know

Melatonin or magnesium: Can either supplement help you sleep?

Understanding orthorexia: Have your healthy eating goals gone too far?
Back Pain Archive
Articles

What to do about pain "down there"?
Chronic pelvic pain-medically known as chronic prostatitis / chronic pelvic pain syndrome, or CP/CPPS-is one of the more common and challenging conditions older men face. Because the underlying cause may not be identified, doctors often take a trial-and-error approach to managing the common symptoms like throbbing, aching pain, urination problems, and sexual dysfunction. Options include different types of medication, physiotherapy, shock wave therapy, and aerobic exercise.

When do I need an imaging test for my back pain?
An x-ray, CT scan, or MRI is usually not needed for addressing low back pain unless people have other symptoms or risk factors for a serious condition. Short-term rest, heat or cold, and over-the-counter medication can ease discomfort until the back pain goes away.
Battle of the bulge
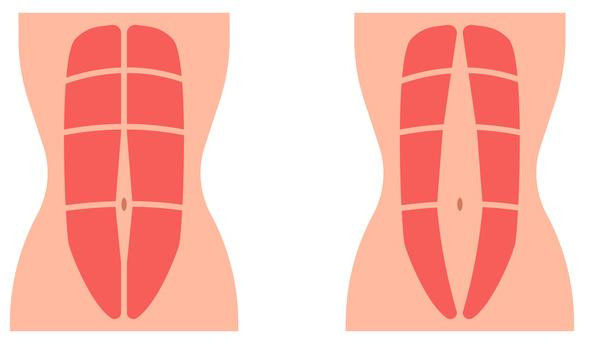
Diastasis recti occurs when the rectus abdominis muscle - the "six-pack" - separates and leads to a midline abdominal bulge. This might happen because of pregnancy, aging, genetics, excessive abdominal pressure, or abdominal surgery. The bulge becomes more noticeable when lifting heavy objects, getting out of bed, or even performing everyday tasks. The condition usually doesn't resolve on its own. Working with a physical therapist can help decrease the muscle separation.

The overlap between back pain and pelvic floor dysfunction
Pelvic floor dysfunction in women is commonly linked to lower back pain. The odds of developing pelvic floor-related back pain increase for women as they get older due to factors such as diminished estrogen and childbirth-related pelvic floor damage. Lower back pain and pelvic floor dysfunction may also have overlapping signs, including urinary leakage or urgency, a feeling of heaviness in the pelvis or vaginal bulging, constipation or bowel issues, painful sex or urination, and pain with prolonged sitting or standing.

Managing chronic back pain
Chronic back pain (pain that lasts more than 12 weeks) can be more challenging to diagnose and treat compared to short-term pain from an injury. The first-line approach is conservative treatment, such as over-the-counter pain medication, physical therapy, and lifestyle changes. However, sometimes these are not enough, and advanced methods are needed. Depending on the source of chronic back pain, these can include stronger prescription medication, corticosteroid injections, and surgery.

Analysis highlights best treatments for neuropathic pain
A 2025 analysis found that tricyclic antidepressants, the anticonvulsants gabapentin (Neurontin) and pregabalin (Lyrica), and serotonin-norepinephrine reuptake inhibitors, such as duloxetine (Cymbalta) were the most effective drug treatments for neuropathic pain.

Walking tied to less back pain
A 2025 study of more than 11,000 people (average age 55), followed for about four years, those who walked more than 100 minutes a day had a 23% lower risk of chronic low back pain, compared with people who walked less than 78 minutes per day.

Topical painkillers for sprains and strains
Topical painkillers might be safer than pills to relieve discomfort from muscle strains (like a pulled hamstring) or ligament sprains (like a sprained ankle). This is because topicals target the area of pain. As a result, other parts of the body are exposed to lower levels of medicine. That's important, since some painkillers, such as nonsteroidal anti-inflammatory drugs (NSAIDs), can pose severe risks-such as heart attack and stroke.

3 do-at-home stretches to release hip and buttock pain
To reduce the pain of aching hip or buttocks muscles, one might consider stretching them. The activity makes muscles healthier and more flexible, which might keep them from pressing against nerves or bursae that can become inflamed and tender. It's best to stretch regularly with static stretches of the muscles at least three to five times per week, after a brief warm-up or a regular exercise routine. If hip or buttock pain flares, doing gentle stretches might ease discomfort in the moment.

The dangerous dismissal of women's pain
Studies show that women's pain experiences are often minimized, dismissed, or undertreated by clinicians. Women and men perceive pain differently. Factors contributing to women's undertreatment for pain include lack of objective pain measures, uncertain diagnoses, clinician bias, and how women are socialized. Women can ensure their pain is taken seriously by communicating closely with clinicians about expectations, stating they recognize their pain may not be 100% relieved, and doing their own research on possible reasons for pain.
Signs of pneumonia: Sometimes vague and unexpected
Using a vibration plate: What it can — and can't — do for your body
The surprising link between ovarian cancer and the fallopian tubes
People who walk more or walk faster live longer, study finds
For sleep apnea, a dental device may be as effective as CPAP
Rosacea treatments: What works?
Carb cycling: What is it, and does it work?
Salmonella, E. coli, Cyclospora, and other germs that cause food poisoning: What you need to know
Melatonin or magnesium: Can either supplement help you sleep?
Understanding orthorexia: Have your healthy eating goals gone too far?
Free Healthbeat Signup
Get the latest in health news delivered to your inbox!
Sign Up
